
|
Getting your Trinity Audio player ready...
|
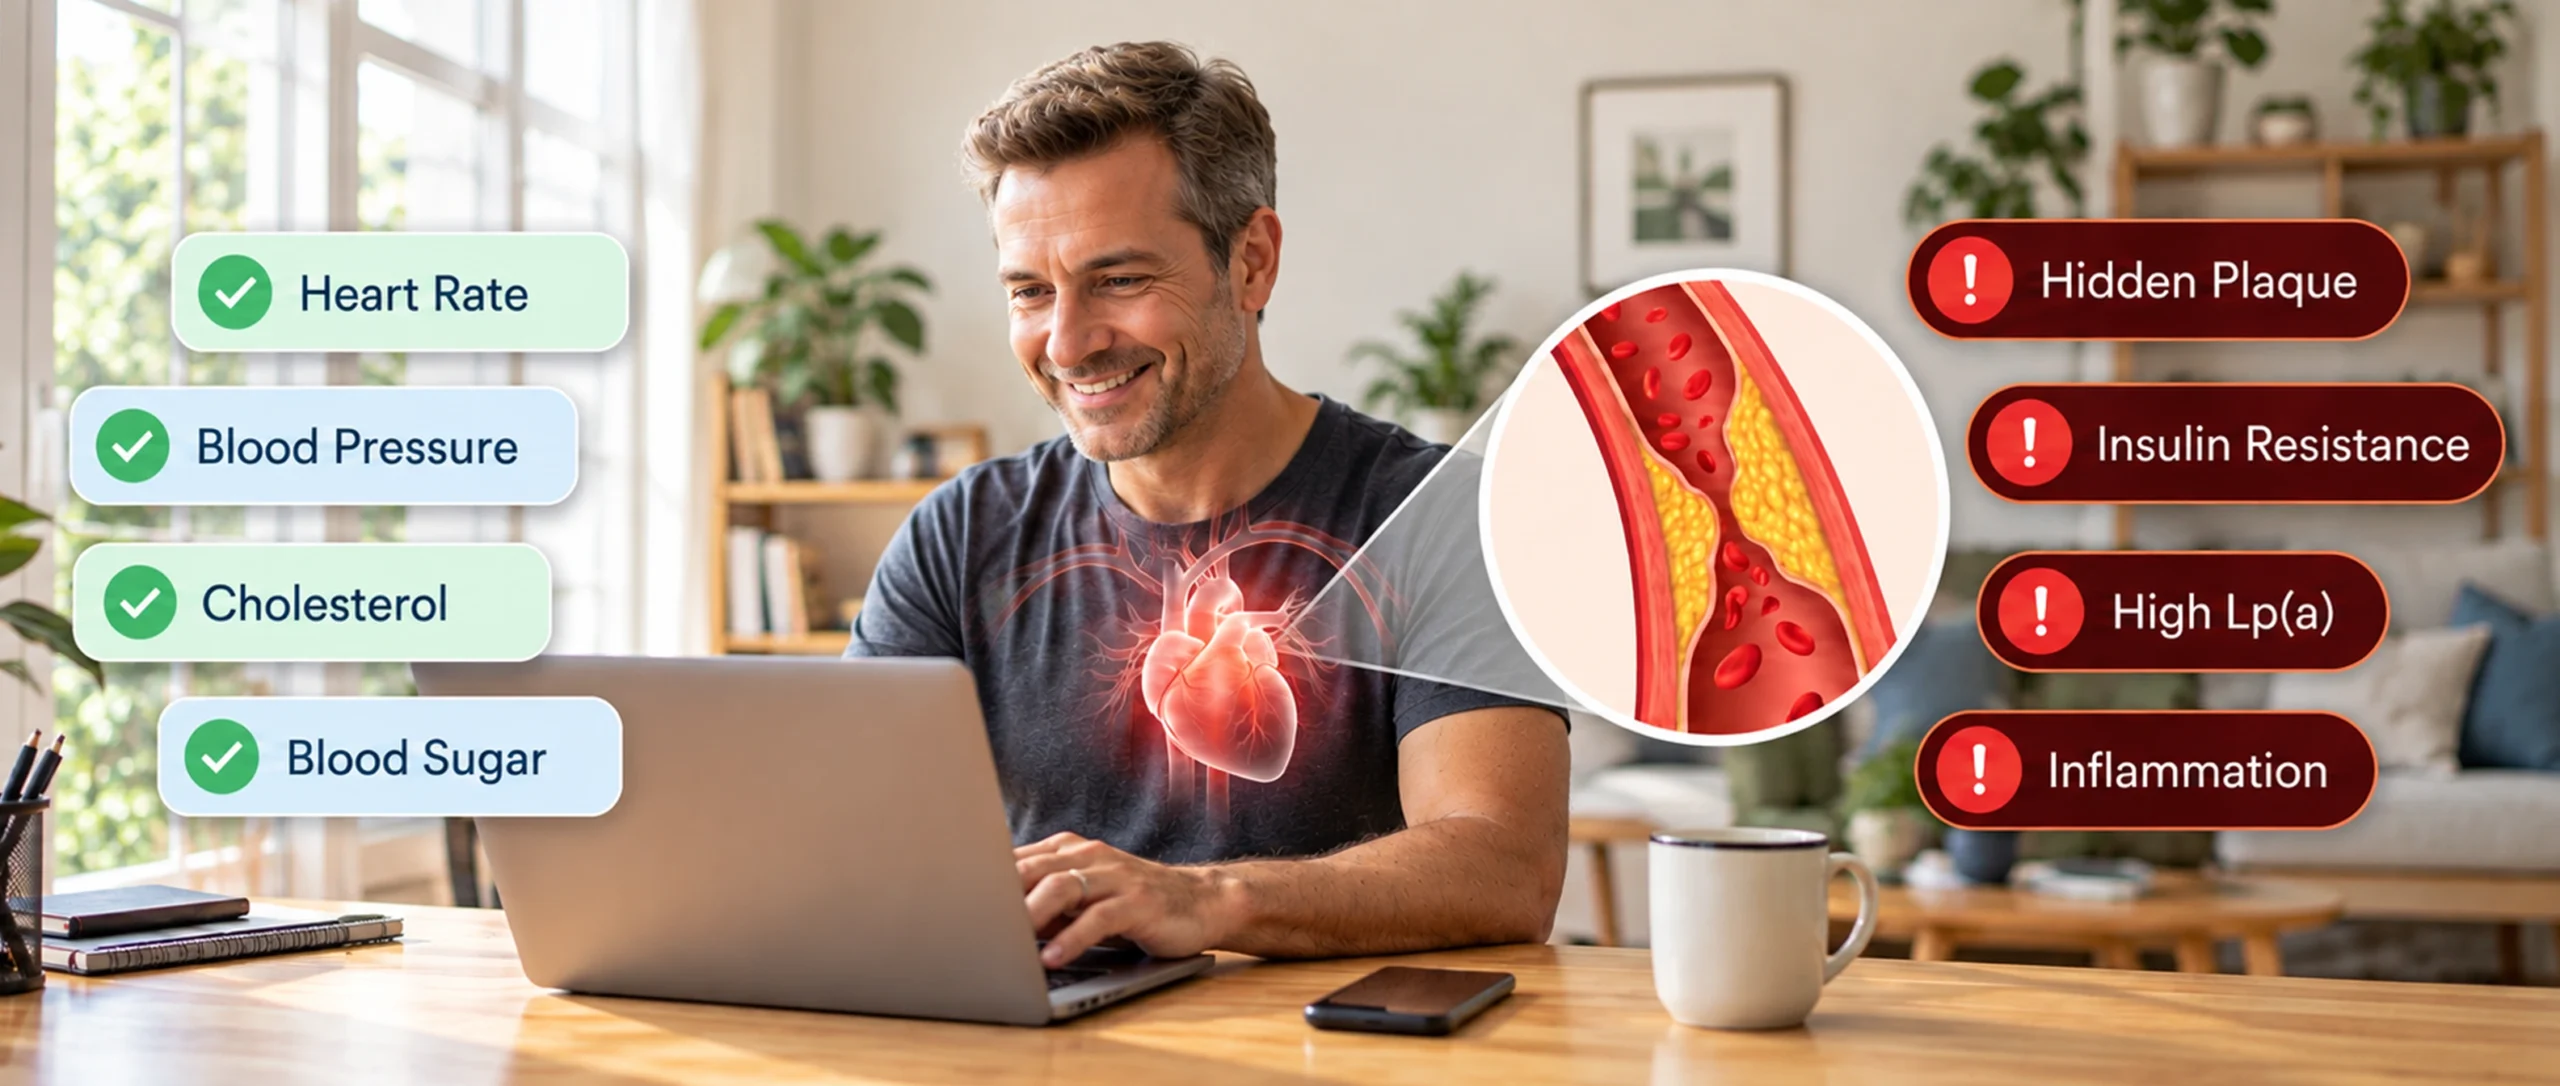
One of the most consequential features of cardiovascular disease is how quietly it can develop.
A person may feel energetic, work long hours, and exercise regularly while hypertension, metabolic dysfunction, or atherogenic lipoprotein exposure increases future risk. The absence of symptoms is useful information, but it is not a complete risk assessment.
Recognizing silent cardiovascular risk factors creates an opportunity to intervene before a crisis makes the problem obvious.
Metabolic health can change gradually.
Insulin resistance occurs when tissues respond less effectively to insulin. The body may compensate for a period before blood glucose becomes clearly abnormal.
Increasing abdominal fat, elevated triglycerides, rising glucose, and blood-pressure changes can appear together. A single normal fasting glucose value does not describe the entire metabolic picture. HbA1c, waist circumference and other clinically selected measurements may help clarify it.
HbA1c reflects average glucose exposure over two to three months, but it does not directly test insulin resistance. Conditions affecting red blood cells can also influence interpretation.
Blood pressure often gives no warning.
Hypertension can be present without headaches, dizziness or any obvious change in wellbeing. Over time, persistent elevation increases the risk of stroke, heart disease and kidney damage.
Accurate measurement is essential. A pattern of readings obtained with a validated upper-arm monitor can help distinguish persistent hypertension from an isolated office elevation. Out-of-office readings may also reveal hypertension that is missed in the clinic.
Lipid risk includes inherited factors.
LDL cholesterol remains central to lipid assessment. In select patients, ApoB offers additional information about the number of circulating atherogenic particles, especially when triglycerides or metabolic disease complicate the picture.
Lp(a) identifies a different risk pathway. Its concentration is largely genetically determined. A high level can be present in someone who eats well, exercises, and has no metabolic abnormalities.
Current guidance recommends measuring Lp(a) at least once in adulthood. Knowing the result can inform the intensity of overall risk management and whether family members should discuss testing with their clinicians.
Inflammation needs context
Inflammation plays an important role in atherosclerosis. A blood test called high-sensitivity C-reactive protein (hs-CRP) may provide additional context when assessing cardiovascular risk.
However, hs-CRP is nonspecific. Levels can rise because of infection, inflammatory conditions, recent illness, or other causes. A high result does not diagnose coronary plaque or prove that inflammation is coming from the heart.
The result is most useful when interpreted alongside your overall cardiovascular risk, symptoms, medical history, and other clinical findings.
Silent Cardiovascular Risk Factors Do Not Follow One Fixed Sequence
Cardiovascular risk factors often interact rather than follow a single, predictable sequence. Metabolic dysfunction, inflammation, insulin resistance, hypertension, and lipid abnormalities can influence one another, but they do not form a universal chain in which one condition inevitably leads to the next.
For example, some people may not have diabetes but may still develop hypertension, while others may have inherited elevated Lp(a) without insulin resistance. Several cardiovascular and metabolic pathways may be amplified because of kidney disease.
The 2026 cardiovascular-kidney-metabolic (CKM) guideline stresses these interconnected risks while recognizing that cardiovascular risk should be assessed individually, not through a one-size-fits-all progression.
Biomarkers and Plaque Answer Different Questions
Laboratory tests can help characterize cardiovascular risk, but they do not directly show the condition of the coronary arteries.
When appropriate, selected imaging tests can help determine whether atherosclerosis is present or provide additional information when treatment decisions are uncertain. Whether imaging is useful depends on factors such as symptoms, age, overall cardiovascular risk, previous test results, and whether the findings would change management. Routine coronary scanning is not recommended for every asymptomatic adult.
A right approach is to put all the pieces together: family history, blood pressure, lipid levels, metabolic and kidney health, lifestyle, and fitness. From there, the next test or intervention can be identified deliberately rather than simply adding more testing.
Silent cardiovascular risk factors are not a reason for fear. It is a reason to ask better questions earlier, and to act on the answers that can change the future.